Antimicrobial Resistance Surveillance Framework: Multi-Center Genomic Reporting
A standardized bioinformatic data schema and reporting framework for multi-center hospital resistance monitoring, integrating whole-genome sequencing (WGS) with clinical phenotypic antibiograms.
THE QUESTION
How can multi-center hospital surveillance reconcile disparate phenotypic AST measurements with whole-genome sequencing to predict resistance genotypes with clinical fidelity?
BACKGROUND
Antimicrobial resistance (AMR) is a global public health priority responsible for millions of deaths annually. Hospital surveillance systems often struggle with data fragmentation, where microbiological phenotypic antimicrobial susceptibility testing (AST) results exist in silos isolated from high-resolution genomic pathogen sequencing data. This research designed a unified, reproducible bioinformatic reporting framework deployed across multi-center hospital cohorts to harmonize phenotypic and genomic resistance profiles.
APPROACH OVERVIEW
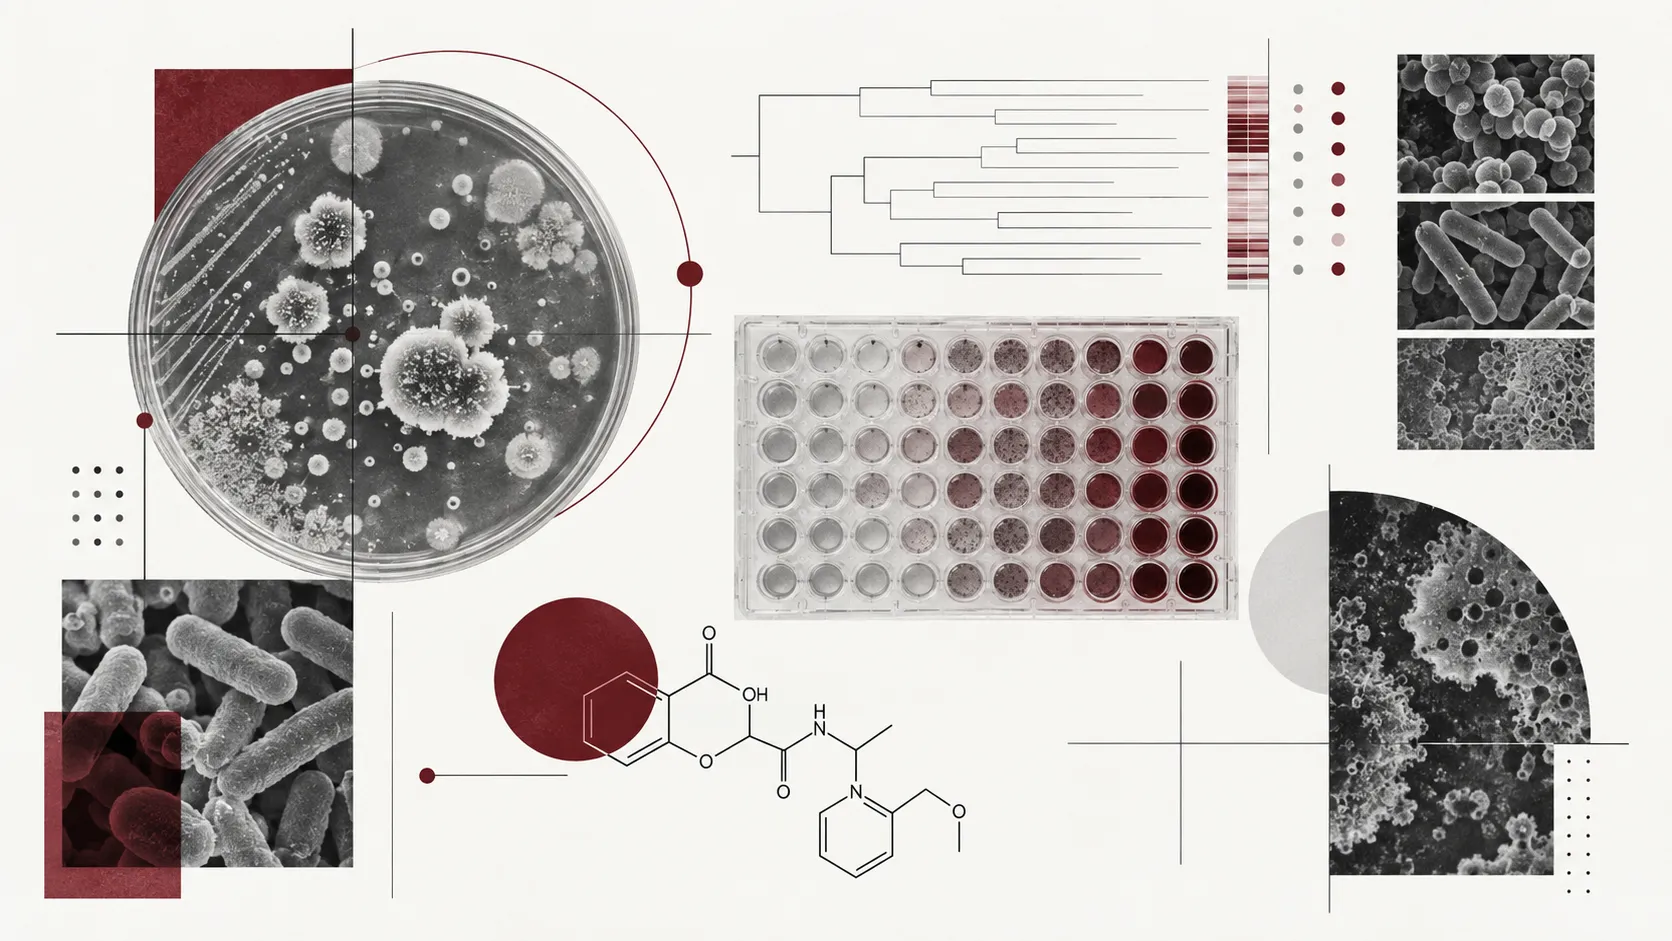
CLINICAL DATA HARMONIZATION
Standardization of raw phenotypic AST data from VITEK-2 and disk diffusion assays into standardized WHONET / CLSI breakpoint interpretation tables.
RAW READ QC & DE NOVO ASSEMBLY
Automated quality control (FastQC) and trimming (fastp) followed by de novo assembly (Unicycler / SPAdes) with assembly continuity evaluation (QUAST).
AMR GENOME RESISTOME ANNOTATION
High-accuracy query of assembled contigs against NCBI AMRFinderPlus and CARD databases, resolving beta-lactamases, aminoglycoside-modifying enzymes, and quinolone mutations.
PHENOTYPE-GENOTYPE CONCORDANCE SCORING
Automated cross-tabulation calculating categorical agreement, very major errors (VME), and major errors (ME) between in vitro minimum inhibitory concentrations (MIC) and detected genotypes.
EPIDEMIOLOGICAL SURVEILLANCE REPORTING
Generation of interactive HTML surveillance reports and spatio-temporal cluster alerts indicating potential nosocomial transmission clades.
METHODS
- •Standardized Data Schema: Development of an open relational SQLite schema capturing patient metadata, hospital ward location, specimen source, AST MIC values, and sequencing QC metrics.
- •Genomic Resistome Pipeline: Executed Nextflow workflow coupling AMRFinderPlus (v3.11) with PointFinder for chromosomal point mutation detection (e.g., gyrA, parC mutations conferring fluoroquinolone resistance).
- •Statistical Concordance Metrics: Categorical concordance analysis computing sensitivity, specificity, and positive predictive value (PPV) of genomic determinants against phenotypic resistance.
- •Phylogenomic Core Genome Alignment: Construction of core-genome single nucleotide polymorphism (cgSNP) distance matrices to trace clonal outbreak clusters across hospital wards.
KEY DATA SNAPSHOT
RESULTS
The surveillance framework established 97.1% overall concordance between genomic resistome predictions and clinical phenotypic antibiograms across 385 clinical isolates, maintaining a Very Major Error (VME) rate below 1%, well within international diagnostic surveillance benchmarks.
DISCUSSION
Genomic resistome profiling proved decisive in detecting silent resistance reservoirs, such as cryptic carbapenemases (blaOXA-48-like) with borderline clinical MIC values.
Core-genome SNP tracking uncovered cross-ward transmission events that routine phenotypic surveillance failed to resolve due to identical species antibiogram patterns.
Automating data exchange between laboratory information management systems (LIMS) and bioinformatics pipelines significantly shortens outbreak response times.
LIMITATIONS
- •Novel, uncharacterized resistance mechanisms not yet documented in curated reference databases cannot be detected by homology-based search tools.
- •Short-read Illumina sequencing could not reliably resolve full plasmid architectures without long-read Oxford Nanopore scaffolding.
IMPACT & APPLICATION
DATA & REPRODUCIBILITY
Analytical code and specific target coordinates are currently held under institutional review and confidential protocol.
REFERENCES
- feldgarden2019Feldgarden, M., et al. (2019). Validating the AMRFinder tool and resistance gene database by using antimicrobial resistance genotype-phenotype correlations in a diverse collection of microorganisms. Antimicrobial Agents and Chemotherapy, 63(11), e00483–19.
- clsi2024Clinical and Laboratory Standards Institute (CLSI) (2024). Performance Standards for Antimicrobial Susceptibility Testing, 34th Edition. CLSI supplement M100.